After completing this note you will be able to describe the clinical approach to Parkinson disease, list relevant local aetiologies, recognise key examination findings, interpret basic investigations and outline immediate and definitive management – remembering to verify doses and local protocols against the Kenya MoH guideline and your hospital formulary.
Definition
Parkinson disease (PD) is a progressive neuro‑degenerative disorder characterised by the loss of dopaminergic neurons in the substantia nigra pars compacta, leading to a classic motor syndrome of bradykinesia, rigidity, resting tremor and postural instability, often accompanied by non‑motor features.
Anatomy and physiology you need
- Basal ganglia circuitry – striatum (caudate & putamen), globus pallidus interna/externa, subthalamic nucleus, substantia nigra.
- Dopaminergic pathway – nigrostriatal tract: dopamine from substantia nigra pars compacta modulates the direct (facilitatory) and indirect (inhibitory) basal ganglia pathways, balancing movement initiation and inhibition.
- Neurotransmitter interplay – dopamine loss → relative excess of acetylcholine, glutamate and GABA, producing rigidity and tremor.
- Motor cortex output – altered basal ganglia output to thalamus changes cortical motor planning, manifesting as bradykinesia.
Causes and risk factors
| Category | Relevant factors in Kenya |
|---|---|
| Idiopathic | Age >60, male sex, family history of PD |
| Genetic | LRRK2, PARK2 mutations (rare, but reported) |
| Secondary / vascular | Stroke, chronic hypertension, HIV‑associated neurodegeneration |
| Infectious | TB meningitis sequelae, cerebral malaria, neurocysticercosis |
| Autoimmune / inflammatory | Post‑infectious encephalitis, rheumatic fever (rare) |
| Hematologic | Sickle cell disease with chronic hypoxia |
| Toxin exposure | Pesticides (organophosphates), heavy metals, manganese (found in mining areas) |
| Drug‑induced | Antipsychotics, metoclopramide, some anti‑emetics |
Pathophysiology
Loss of dopaminergic neurons → ↓ dopamine in striatum → ↓ stimulation of direct pathway & ↑ inhibition of indirect pathway → ↑ output from globus pallidus interna → ↓ thalamic excitation of motor cortex → bradykinesia & rigidity
↓ dopamine → relative ↑ acetylcholine → tremor
Neuroinflammation (HIV, TB, malaria) & oxidative stress → accelerates neuronal loss
Genetic mutations → abnormal protein aggregation (α‑synuclein) → Lewy body formation → neuronal death
Environmental toxins → mitochondrial dysfunction → apoptosis of nigral cells.
Clinical features
| Aspect | Key questions for the history | Why it matters / pathophysiologic link |
|---|---|---|
| Motor symptoms | • Onset – when did the tremor or stiffness first appear?<br>• Resting tremor – is it unilateral, “pill‑rolling”, improves with action?<br>• Bradykinesia – do you notice slowness in getting up, dressing, eating?<br>• Rigidity – any “cogwheel” feel, stiffness that is present in all directions?<br>• Postural instability – have you had falls, difficulty turning, trouble with balance?<br>• Fluctuations – do symptoms vary during the day or with stress? | Resting tremor, bradykinesia and rigidity are the classic triad that reflect loss of dopaminergic input to the basal ganglia. Postural instability appears later when compensatory pathways fail. |
| Non‑motor symptoms | • Sleep – vivid dreams, REM behaviour disorder, insomnia?<br>• Autonomic – constipation, urinary urgency, orthostatic dizziness, erectile dysfunction?<br>• Neuropsychiatric – depression, anxiety, apathy, hallucinations?<br>• Cognitive – memory lapses, difficulty planning, “brain fog”? | Autonomic and neuropsychiatric features stem from widespread Lewy body deposition and loss of non‑dopaminergic nuclei. Early recognition improves quality of life and may influence drug choice (e.g., avoid anticholinergics in cognitive impairment). |
| Medication history | • Prior use of antipsychotics, metoclopramide, or other dopamine‑blocking drugs?<br>• Exposure to neurotoxins (pesticides, manganese)? | Drug‑induced parkinsonism mimics idiopathic disease but often improves on withdrawal; important for reversible causes. |
| Risk factors specific to Kenya | • HIV status, TB treatment history, malaria episodes, sickle‑cell disease, rheumatic fever, occupational exposure to pesticides?<br>• Family history of parkinsonism or early‑onset disease? | Infections (HIV, TB meningitis) and chronic inflammation can precipitate secondary parkinsonism. Pesticide exposure is a recognized environmental risk. |
| Functional impact | • Ability to perform ADLs (feeding, grooming, walking)?<br>• Need for assistive devices?<br>• Driving safety? | Determines disease stage, need for physiotherapy, occupational therapy, and safety counseling. |
Examination findings and their rationale
| Examination component | Expected finding in Parkinson disease | Why it occurs |
|---|---|---|
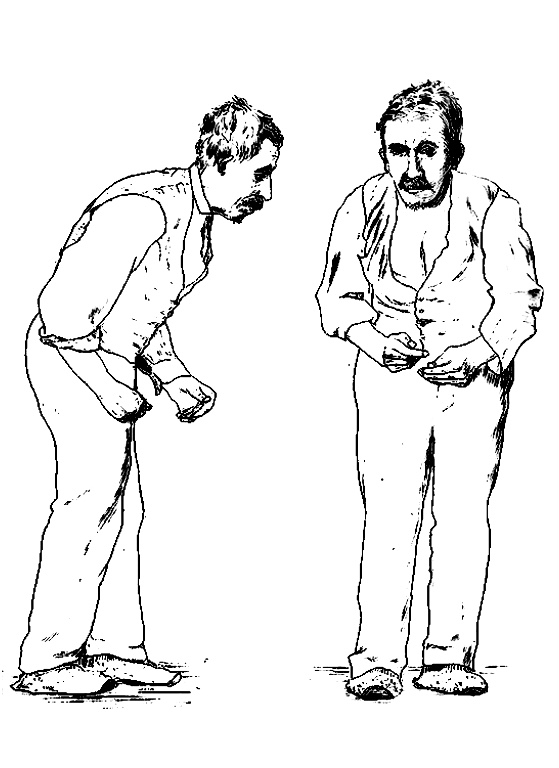
| General observation | Reduced arm swing, stooped posture, shuffling gait | Loss of automatic movement scaling from basal ganglia output. |
| Tremor assessment | Resting tremor, unilateral at onset, “pill‑rolling” 4–6 Hz, diminishes with purposeful movement | Disinhibition of the thalamocortical loop due to dopaminergic loss. |
| Rigidity testing | Increased tone throughout range, “cogwheel” quality when passively moved | Intermittent stretch‑reflex activation from basal ganglia dysfunction. |
| Bradykinesia | Slowness of finger tapping, reduced amplitude of repetitive movements, delayed initiation of gait | Impaired facilitation of motor programs. |
| Postural reflexes | Positive pull test (patient takes a step backward to prevent falling) | Failure of automatic postural adjustments. |
| Facial expression | Masked facies, reduced blink rate | Diminished dopaminergic drive to facial nuclei. |
| Speech | Soft, monotone, hypophonic voice | Reduced motor output to laryngeal muscles. |
| Autonomic exam | Orthostatic drop in BP, dry skin, reduced sweating | Involvement of autonomic nuclei and peripheral sympathetic fibers. |
| Cognitive screen (e.g., MoCA) | May show mild executive dysfunction | Early cortical Lewy body spread. |
Differential diagnosis
| Condition | Points toward it | Distinguishing features |
|---|---|---|
| Idiopathic Parkinson disease | Gradual onset, unilateral resting tremor, progressive bradykinesia, good levodopa response | Presence of classic triad, absence of red‑flag features (e.g., early autonomic failure, rapid progression) |
| Drug‑induced parkinsonism | Recent exposure to dopamine antagonists, antipsychotics, metoclopramide | Tremor often symmetric, less bradykinesia, improves after drug withdrawal |
| Vascular parkinsonism | Stepwise progression, history of cerebrovascular disease, gait predominance | MRI shows multiple lacunes, rigidity > tremor, poor levodopa response |
| Progressive supranuclear palsy | Early falls, vertical gaze palsy, axial rigidity | Supranuclear gaze limitation, rapid progression, poor levodopa response |
| Multiple system atrophy | Prominent autonomic failure, cerebellar signs, early urinary dysfunction | MRI may show hot‑cross‑bun, poor levodopa response |
| HIV‑associated parkinsonism | HIV positivity, opportunistic infections, CD4 count low | Improves with antiretroviral therapy, may have concurrent neurocognitive deficits |
| Post‑TB meningitis parkinsonism | History of TB meningitis, basal ganglia calcifications | Imaging shows basal ganglia lesions, often asymmetric |
| Malaria‑related extrapyramidal syndrome | Recent severe malaria, especially cerebral malaria | Temporal relation to infection, may improve with antimalarial treatment |
| Sickle‑cell neurovascular disease | Sickle‑cell disease, recurrent vaso‑occlusive crises, MRI lesions | Stroke‑related deficits, often focal rather than diffuse |
Investigations
| Test | What it answers | Interpretation |
|---|---|---|
| MRI brain (T1/T2/FLAIR) | Structural lesions, vascular changes, basal ganglia calcifications | Normal or mild age‑related changes support idiopathic PD; lacunes → vascular PD; calcifications → post‑TB or metabolic causes |
| DaT‑SPECT (DAT scan) | Dopamine transporter integrity | Reduced uptake confirms presynaptic dopaminergic loss; normal scan suggests drug‑induced or psychogenic parkinsonism |
| CBC, ESR, CRP | Inflammatory or infectious activity | Elevated ESR/CRP may point to TB, HIV, or systemic infection |
| Serology: HIV, VDRL, malaria rapid test | Presence of specific infections | Positive HIV → consider HIV‑related parkinsonism; malaria positive in recent severe infection |
| Serum ferritin, copper, ceruloplasmin | Metabolic causes (hemochromatosis, Wilson disease) | Abnormal levels suggest alternative treatable causes |
| Urine toxicology | Exposure to neurotoxins (e.g., manganese) | Positive result supports toxic parkinsonism |
| Neuropsychological screen (MoCA) | Cognitive involvement | Scores <26 indicate cognitive impairment, may sway toward atypical parkinsonism |
| Orthostatic vitals | Autonomic dysfunction | Drop >20 mmHg systolic on standing suggests autonomic failure, common in MSA |
Diagnosis and severity
Diagnostic criteria (clinical)
- Bradykinesia plus at least one of: resting tremor, rigidity, or postural instability.
- Exclusion of secondary causes by history, examination, and targeted investigations (imaging, labs).
- Supportive features (e.g., unilateral onset, progressive course, good response to dopaminergic therapy).
If the above are met and no red‑flag signs (early severe autonomic failure, rapid progression, cerebellar signs) are present, a diagnosis of idiopathic Parkinson disease is made.
Severity staging (Hoehn & Yahr)
| Stage | Clinical picture | Management implication |
|---|---|---|
| 1 | Unilateral involvement, minimal disability | Initiate lifestyle measures, consider early levodopa or MAO‑B inhibitor if functional impact |
| 2 | Bilateral signs, no balance impairment | Add dopamine agonist if needed; physiotherapy for gait |
| 3 | Early postural instability, still independent | Introduce levodopa, monitor for dyskinesia; safety counseling (fall prevention) |
| 4 | Severe disability, still able to walk with aid | Optimize levodopa, consider adjunctive COMT inhibitor; refer for occupational therapy |
| 5 | Wheelchair bound or bedridden | Palliative approach, manage non‑motor symptoms aggressively, consider deep brain stimulation if still ambulatory and medication‑responsive |
Severity guides pharmacologic choice (early disease – MAO‑B inhibitors or dopamine agonists to delay levodopa; later disease – levodopa ± adjuncts) and non‑pharmacologic interventions (physio, speech therapy, occupational therapy, fall‑prevention programs).
Monitoring includes regular assessment of motor scores (UPDRS), cognitive screening, orthostatic vitals, and medication side‑effects (e.g., hallucinations, impulse control disorders). Safety measures—home hazard reduction, driving evaluation, and caregiver education—are essential at each stage.
Management
| Phase | Goal | Key actions | Safety / contraindications |
|---|---|---|---|
| Immediate stabilisation | Prevent falls, treat acute motor crises, address autonomic emergencies | • Place patient in a safe, low‑risk environment (bed rails, non‑slip footwear) <br>• Treat severe rigidity or “off” state with rapid‑acting dopaminergic agents (e.g., sub‑cutaneous apomorphine) if available <br>• Correct dehydration, electrolyte imbalance, urinary retention, or constipation <br>• Review current meds for dopamine‑blocking agents (antipsychotics, metoclopramide) and stop them | Apomorphine contraindicated in severe cardiovascular disease, uncontrolled hypertension, or hypersensitivity. |
| Definitive pharmacologic therapy | Re‑establish dopaminergic tone, improve motor function, control non‑motor symptoms | • Levodopa/Carbidopa – mainstay for most patients; start low, titrate slowly to avoid dyskinesia. <br>• Dopamine agonists (e.g., pramipexole, ropinirole) – useful in younger patients or as levodopa‑sparing agents. <br>• MAO‑B inhibitors (selegiline, rasagiline) – modest symptom control, neuroprotective rationale. <br>• COMT inhibitor (entacapone) – add when levodopa wearing‑off appears. <br>• Anticholinergics (trihexyphenidyl, benztropine) – for prominent tremor in younger patients; avoid in older adults with cognitive impairment. <br>• Amantadine – for dyskinesia or mild motor benefit. | Avoid dopamine antagonists (typical antipsychotics, metoclopramide). Anticholinergics contraindicated in glaucoma, urinary retention, severe cognitive decline. |
| Non‑pharmacologic measures | Optimize function, reduce complications | • Physiotherapy: gait training, balance exercises, stretching. <br>• Occupational therapy: adaptive utensils, dressing strategies. <br>• Speech‑language therapy for dysarthria and swallowing. <br>• Regular aerobic activity to improve mood and cognition. | Ensure exercises are supervised initially to prevent falls. |
| Monitoring & follow‑up | Detect motor fluctuations, side‑effects, disease progression | • Review motor score (UPDRS/MDS‑UPDRS) every 6–12 months. <br>• Screen for dyskinesia, hallucinations, orthostatic hypotension, constipation, depression. <br>• Laboratory: liver function (amantadine), renal function (levodopa metabolites), CBC if on MAO‑B inhibitors with antidepressants. <br>• Adjust therapy based on “on/off” patterns and patient‑reported quality of life. | Watch for serotonin syndrome when MAO‑B inhibitors are combined with SSRIs. |
Complications and prognosis
| Complication | Typical onset | Clinical impact | Management tip |
|---|---|---|---|
| Motor fluctuations (wearing‑off, “on/off”) | 3–5 years on levodopa | Unpredictable mobility, falls | Add COMT inhibitor or adjust levodopa dosing interval |
| Dyskinesias | After several years of levodopa | Involuntary choreic movements, may limit activities | Reduce levodopa dose, add amantadine |
| Orthostatic hypotension | Early or late disease | Dizziness, syncope, falls | Encourage slow position changes, increase salt/fluid, consider fludrocortisone |
| Neuropsychiatric (depression, hallucinations, psychosis) | Variable | Reduced adherence, caregiver burden | Treat depression with SSRIs (avoid MAO‑B overlap), use low‑dose quetiapine for psychosis |
| Swallowing dysfunction & aspiration pneumonia | Advanced stage | Major cause of mortality | Speech therapy, diet modification, consider PEG if severe |
| Cognitive decline/dementia | Late stage | Loss of independence | Cholinesterase inhibitors may help; avoid anticholinergics |
| Falls & fractures | Throughout disease | Morbidity, mortality | Fall‑prevention program, bone health assessment, vitamin D/calcium |
Prognosis – Parkinson disease is progressive; median survival after diagnosis is roughly 10–15 years, but many patients maintain functional independence for many years with optimal therapy. Early recognition of complications and multidisciplinary care improve quality of life.
High‑yield exam points
- Look‑alike conditions: drug‑induced parkinsonism (antipsychotics, metoclopramide), essential tremor, progressive supranuclear palsy, multiple system atrophy, vascular parkinsonism.
- Common wrong first step: prescribing an antipsychotic for tremor without checking for underlying Parkinsonism.
- Bedside examiner questions:
- “What feature distinguishes Parkinson tremor from essential tremor?” (resting, improves with action).
- “Explain why you would stop a patient’s metoclopramide.” (dopamine blockade).
- “How does the ‘pull‑test’ help you assess postural stability?” (quantifies retropulsion).
- “What non‑motor symptom would make you consider starting an SSRI?” (depression).
Clinical case
Case: 62‑year‑old male farmer presents with a 2‑year history of left‑hand resting tremor, bradykinesia, and shuffling gait. He reports occasional constipation and a recent episode of mild visual hallucinations after starting levodopa. No history of antipsychotic use. Examination shows cogwheel rigidity, reduced arm swing, positive pull‑test, and MMSE 27/30.
Questions
- What is the most likely explanation for his hallucinations?
Answer: Dopaminergic overstimulation from levodopa therapy; consider dose reduction or add a low‑dose atypical antipsychotic (e.g., quetiapine).
- Which medication would you add to reduce “off” periods without worsening hallucinations?
Answer: A COMT inhibitor (entacapone) to prolong levodopa effect while keeping the same dose.
- What safety advice should you give regarding his driving?
Answer: Advise temporary cessation of driving until motor fluctuations are controlled and a formal driving assessment is performed, due to risk of sudden “off” episodes and impaired postural reflexes.
Practice questions
Question 1
A 58‑year‑old woman with newly diagnosed Parkinson disease is started on levodopa/carbidopa. Two weeks later she develops severe nausea and vomiting. What is the most appropriate next step?
A. Add an anticholinergic drug
B. Switch to a dopamine agonist
C. Give a low‑dose anti‑emetic that does not block dopamine
D. Increase the levodopa dose
Answer: C. Use a dopamine‑sparing anti‑emetic (e.g., ondansetron) to control symptoms without worsening parkinsonism.
Question 2
A patient on long‑term levodopa presents with involuntary writhing movements of the limbs that appear only when the medication is at peak effect. Which intervention is most likely to reduce these movements?
A. Reduce levodopa dose and add amantadine
B. Add a higher dose of levodopa
C. Start an anticholinergic agent
D. Switch to a monoamine oxidase‑B inhibitor only
Answer: A. Lowering the levodopa peak and adding amantadine helps control peak‑dose dyskinesia.
Question 3
A 70‑year‑old man with Parkinson disease develops orthostatic dizziness. His blood pressure supine is 130/80 mm Hg and drops to 100/60 mm Hg after 3 minutes standing. Which measure is first‑line?
A. Start fludrocortisone
B. Advise increased fluid and salt intake
C. Prescribe midodrine immediately
D. Add a dopamine agonist
Answer: B. Simple non‑pharmacologic measures (hydration, salt) are first‑line for orthostatic hypotension.
Question 4
A patient on chronic antipsychotic therapy for schizophrenia develops a resting tremor and bradykinesia. Which statement is correct?
A. This is likely essential tremor; start propranolol
B. The antipsychotic is causing drug‑induced parkinsonism; consider switching to a drug with lower D2 affinity
C. Initiate levodopa immediately
D. Add an MAO‑B inhibitor to improve symptoms
Answer: B. Dopamine‑blocking antipsychotics can cause secondary parkinsonism; switching agents is preferred.
Question 5
During a bedside exam, a student is asked to perform the “pull‑test.” What does a positive result indicate?
A. Cerebellar ataxia
B. Peripheral neuropathy
C. Impaired postural reflexes typical of Parkinson disease
D. Normal finding in healthy adults
Answer: C. A positive pull‑test reflects deficient postural stability, common in Parkinson disease.
Drafted with AI assistance from standard references and reviewed for structure. Check details against your lecture notes and the Kenya MoH guideline.